Malaria and Anaemia (Anemia) of Children in Uganda

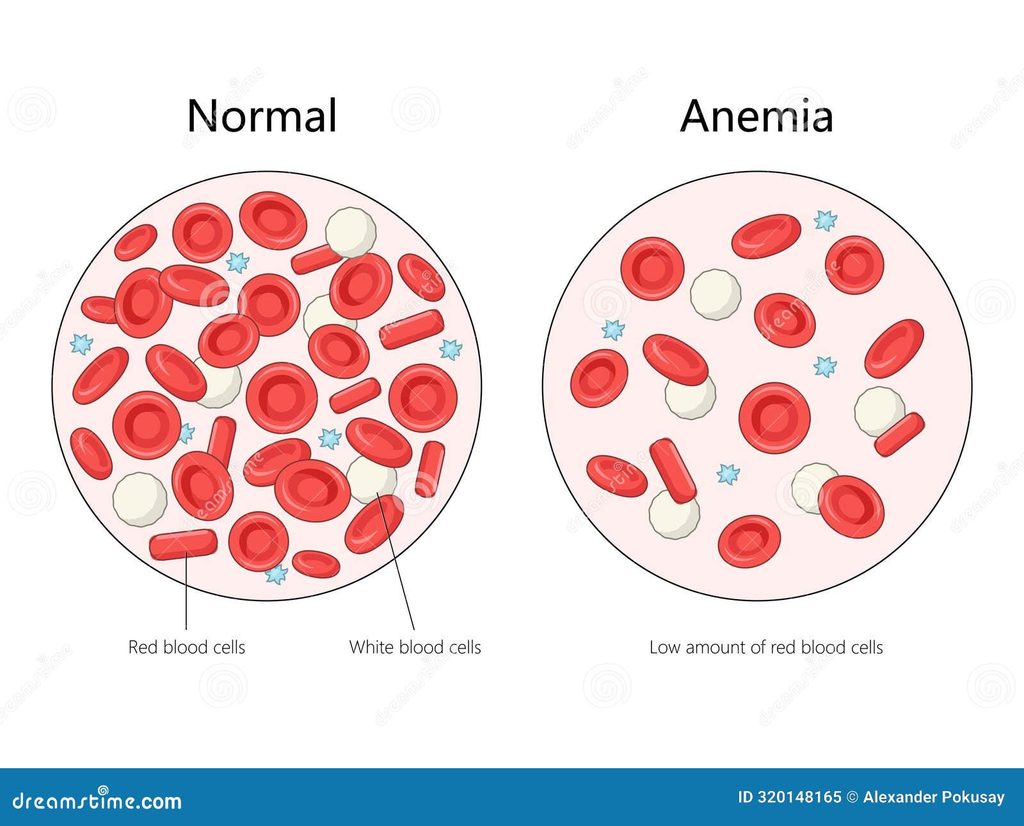
We first addressed the link between anaemia, often caused by malnutrition, and malaria from a study in Ghana in January. Again this week in MalariaWorld there is a study linking the two ailments in Uganda. ‘Co-occurrence of anaemia and malaria among children under five in Uganda: A joint modeling analysis’ by Kakaire et al found 13.8% of children experienced both illnesses simultaneously, more than double the 6.4% of the Ghana study.

Anaemia was tested on blood samples collected from each child aged 6–59 months using a spring-loaded, sterile lancet to make a finger or heel-prick. The drop of blood was collected in a microcuvette, and the Haemoglobin level analysed using a portable HemoCue analyser. The results were available within 10 min and were given to the child’s parent or guardian verbally and in writing. Parents were encouraged to take the children with haemoglobin level less than 11 g/dl to the nearest healthcare facility for the follow-up.

Malaria was tested by microscopy involved preparing both thick and thin blood smears using 2% Giemsa stain. As a quality control measure, each smear was read by two independent expert microscopists who were not involved with the participant respondent interview. A third reader was only involved to settle parasite presence discrepancy between the two readers. A positive smear parasite density (parasites/µl) was estimated by counting the number of asexual parasites per 200 white blood cells, assuming a white blood cell count of 8000 cells/µl. A smear was only considered negative if no parasites were seen after viewing 100 high-powered fields.

The total number of children 6-59 months with both tests included in the study was 5,755. 2,849 (49.5%) had neither condition, 1,249 (21.7%) had anaemia only, 863 (15.0%) had malaria only, and 794 (13.8%) had both malaria and anaemia. This, though high, was lower than the overlap seen in other studies, e.g. using Uganda MIS 2009 data found 77.0% anaemia among malaria-positive children and 64.9% malaria positivity among anaemic children.

The authors blame the overlap on malaria weakening the children resulting in anaemia. However, childhood anaemia is often caused by iron and other micronutrient deficiencies. We feel that this overlap is evidence that malnutrition is also an underlying factor for malaria. The plasmodia are cleaning up damaged cells caused by malnutrition or poisoning.

Nutrition and Malaria

It is our contention that poor nutrition, either absence of nutrients or consumption of contaminated food or poisons, is a major contributor to the occurrence and severity of malaria. This is always the first topic we seek in MalariaWorld or other regular publications. And this week we were pleased to see in LinkedIn that this week there was a micronutrient conference in Ghana. It does not look like malaria was an issue addressed directly, but perhaps in the future it will be.

It has been three months since we featured articles from MalariaWorld that directly addressed malaria and nutrition.  ‘Burden and co-occurrence of anemia, micronutrient deficiencies, inflammation, and malaria among women, adolescents, and children in Madagascar: a national cross-sectional survey’ by Rohner et al was published in The Journal of Nutrition featured on June 5. ‘The gut microbiome in early life predicts malaria susceptibility’ by Dutton et al was featured on July 10. More recently we also addressed the more general linkage to poverty that may suggest poor nutrition on July 31 and August 7. But nothing since.

Clearly nutrition is not a topic of major interest to mainstream malaria researchers. And this week there is link in MalariaWorld to the new World Health Organisation guidelines on malaria (September 2026). We searched for ‘nutrition’ in the 494 page pdf and found just four references. None addressed any linkage to occurrence or severity of malaria.  ‘Larvivorous fish can serve as an additional source of nutrition’ was one. The second suggested combining Intermittent preventive treatment of malaria in school-aged children in schools that provide nutrition services! The third reference was a word in the title of a steering committee member and fourth in the name, J. Nutrition, in a reference.

Malnutrition gets six hits, but all six in a paragraph with heading ‘Optimal antimalarial dosing in malnourished young children’. It admits ‘Studies of SP in IPTp and of amodiaquine monotherapy and dihydroartemisinin + piperaquine for treatment suggest reduced efficacy in malnourished children’, but nonetheless concludes ‘Although these findings are concerning, they are insufficient to warrant dose modifications (in mg/kg bw) of any antimalarial drug in patients with malnutrition.’

The effect of nutrition on health is not a money spinner for health providers and so is not likely to be studied. For most of us health problem are caused by too much food. In our case fasting for up to 72 hours or perhaps longer, can have great benefits. But there is little financial incentive for anyone to study it.

Malaria disappears in countries when poverty diminishes. This is unrelated to mosquito numbers or drug programmes.

Malaria and Deforestation in the Amazon

In MalariaWorld this week there is an article linking an increase of malaria to deforestation in the Amazon region. ‘Malaria, Forest Loss, and Sociopolitical Stability in the Amazon’ by Annika Terrana at Georgetown University argues that malaria resurgence in the Amazon is driven as much by failures in environmental governance and land-use policy as by any remaining gaps in health systems. It examines the long-term consequences of resurgence, traces the link between deforestation and transmission, and outlines policy pathways to realign malaria control with ecological realities.

The major issue that contributes to the Malaria increase, increased illegal gold mining, was discussed in this column in May. The article also blames logging, road construction, and frontier expansion which disturb forest ecosystems in ways that may favour malaria-carrying mosquito species. The author also surmises that extractive activities draw in mobile workforces with limited immunity and inconsistent access to healthcare, accelerating malaria transmission risk. As a result, even marginal increases in mining activity are associated with substantial increases in malaria transmission one to two years later. The evidence discussed is the Yanomami territory information discussed in more detail in this column in May.

The article concludes that the ecological drivers of malaria in the Amazon are accelerating rather than stabilizing. Forest loss, climate extremes, and governance gaps are converging to undermine decades of progress toward elimination, with mounting health, economic, and institutional costs.

We suspect that the increase in malaria cases is due to the increased exposure to toxins as a result of mining and potential interferences with the food sources due to the mining and logging activities.

Swamps and Malaria

A greater incidence of malaria has always been associated with wet areas, even before the connection was made to mosquitos. Shakespeare called malaria ague and at his time it was prevalent especially in the relatively swampy East Anglia area of England. The name malaria itself is from Italian for bad air. Its cause was thought to be the bad smelling air associated with rot in swampy areas.

And today in MalariaWorld there are articles associating malaria and swamps. ‘The relationship between swamps and malaria: a review of the studies titled The Sanitary and Social Geography of Turkey’ by Taniş examines data on swamps and malaria from the anti-malaria campaigns implemented in Türkiye during the early Republican period.

The study found that the relationship between swamps and malaria varied considerably across provinces. There was a strong positive association along the Mediterranean and Aegean coasts and in the major river deltas. However, the relationship was substantially weaker in the high-altitude regions of Eastern Anatolia. Furthermore, the effectiveness of swamp-drainage programmes in controlling malaria remained limited due to factors such as fragmented implementation, recurrent flooding, and irrigation projects. The analysis also indicates that agricultural activities, particularly rice cultivation, contributed to the spread of malaria by creating artificial swamp environments.

A second MalariaWorld reference is to ‘Malaria Prevalence Near African Mangroves: Negative Association With Mangrove Extent, but Positive Association With Mangrove Greenness’ by Cruz-Laufer et al. The study claims to be the first multi-country analysis linking African mangrove forests to prevalence of malaria (Plasmodium falciparum). It examined the relationships among mangrove land cover and mangrove vegetation greenness across coastal settlements in 27 African countries, linking satellite-derived land cover, vegetation, and weather data with malaria prevalence records from 11 years, ranging from 1996 to 2020.

They found two key associations. First, increasing mangrove land cover is associated with decreasing malaria prevalence at coarse spatial resolution, refuting the traditional view of mangroves as disease-promoting environments. Second, at fine and coarse spatial resolutions, increasing mangrove health (i.e., greener vegetation) is associated with increasing malaria prevalence.

They hypothesised links between both these observations to mosquitos. The decrease associated with increased cover may be due to less larval development in shade. The increase in greener swamps may be driven by higher mosquito abundance and biodiversity in vegetation-rich mangrove areas. This speculation is contradictory. Sadly, the article is behind a pay-wall so we could not look at it in more detail (some data are available to download as zip file). It would be very useful to examine to see if there are other factors related to the location of the swamps that might point to other factors, especially related to poverty and diet.

Genetically Modified Mosquito Research in Africa

Krystal Birungi, an entomologist with Target Malaria Uganda, working to reduce malaria transmission through innovative mosquito research at the Uganda Virus Research Institute.

A blog post in Nature highlighted in MalariaWorld this week features an African scientist working on genetically modified mosquitos. ‘The Ugandan scientist taking aim at malaria’s mosquitoes’ by Desmond Thompson is Ugandan entomologist Krystal Mwesiga Birungi (pictured). The article is part of a series on Young African Scientists to Watch, commemorating the fifth anniversary of Nature Africa

Birungi works with Target Malaria, whose work in Burkina Faso was discussed in August and September 2025 when their field research was stopped by Ibrahim Traore. She works at the Uganda Virus Research Institute in Entebbe. The article describes her childhood experiences of contracting the illness and the serious bout than nearly killed her younger brother. She became interested in science as a result and studied zoology and botany at Makerere University. Now she works for Target Malaria who is developing genetic technologies to modify malaria-transmitting mosquitos. Our scepticism of this proposed method to combat malaria was also discussed in July and February of this year.

Birungi worries about growing insecticide resistance of mosquitos and changing mosquito behaviour – biting outside when people are not under nets. She also worries that the parasite is becoming less susceptible to frontline drugs.

Target Malaria is investigating genetic approaches designed to suppress populations of malaria-transmitting mosquitos. One strategy uses gene drive to spread a genetic modification that disrupts female fertility, so that females inheriting two copies become sterile, thus gradually reducing populations of the malaria-transmitting insect. This idea makes very little sense in terms of Darwinian evolution theory. Mosquitos produce many eggs and are restricted by larval and adult food sources.  Reducing fertility will have little long-term effect. More offspring of unaffected animals will survive instead.

She discusses the interesting science. CRISPR gene-editing technology provides a mechanism for making such targeted changes to DNA. It uses a specially designed guide RNA molecule to locate a specific sequence in the genome and an enzyme to cut the DNA at that point, allowing scientists to introduce the desired modification very precisely.

Researchers introduce the genetic material and editing machinery into mosquito embryos using extremely fine needles under a microscope. This must be done shortly after the eggs are laid, when the embryos are at the right stage of development, which requires a very steady hand to inject a specific part of the egg without damaging it.

Birungi calls for more of this research to be carried out in Africa. Much of the funding has gone to institutions in the Global North. She calls for more involvement of women. In 2025, she was named a Gates Foundation Goalkeepers Child Health Champion and selected for the 2025–26 Obama Foundation Leaders Africa programme.

We agree with Birungi who rejects the notion that malaria must remain an unavoidable fact of African life. However, we feel that to eliminate malaria more emphasis should be placed on nutrition and hygiene than on exotic ‘bug-hunting’.

Mosquito Transmission Belief is Strongly Established

Several news stories this week reminded us of how difficult a challenge we face in our malaria research. The mosquito transmission hypothesis is deeply engrained. I often ask in comments on LinkedIn articles how the poster ‘knows’ malaria is spread by mosquitos. No one has yet answered.

In Nairobi this week PAMCA (Pan-Africa Mosquito Control Association pamca.org) held it first annual conference in three years. I spend a lot of time in Kenya and applied to present a paper ‘Malaria is Spread by Mosquitos?’ but not surprisingly this organization of research scientists dedicated to vector control and elimination of diseases like malaria declined my abstract.

And this week in MalariaWorld the first article introduces a new Podcast series named “The Mosquito Minute” by the Johns Hopkins Malaria Research called ‘What are mosquitoes?’ (actually 28 minutes). Obviously, the only reason they are so interested is the belief that they are disease vectors. One interesting fact in it is that mosquitos drink just 2-3 microlitres of blood per feed.

Also in MalariaWorld this week are a GAVI blog article and news story ‘German airport workers die from malaria caught from plane-riding mosquito’. Two Frankfurt airport workers died and four are hospitalized with malaria. The Robert Koch Institute (RKI) points to an imported Anopheles mosquito, likely carried in on an aircraft, as the most likely source of the infection. Mosquitos trapped at the airport will be sent to Institute of Tropical Medicine in Antwerp, Belgium for genetic tests to find out more about their origin. If the tests find that all are local German mosquitos, I expect nothing more will be said about it.

Unfortunately, by blaming an imported mosquito the airport authorities are not investigating other potential causes of a very serious illness outbreak that has killed two of its staff. It seems far more likely the outbreak affecting the workers was caused by exposure to an environmental toxin in their work.

The belief in mosquito transmission goes back to the turn of the 19th century when many researchers worked on the hypothesis. Most of the early knowledge was found by Italian Battista Grassi and his team. His railway study is most important. However, Grassi’s work did not have proper controls and he was prone to confirmation bias. It is very strange that his 1901 seminal work ‘studi di uno zoologo sulla malaria’ was not translated into English until I translated it. Get a free pdf from our website or a printed version from Amazon.

However, the same kind of academic politics that affects PAMCA is not new. The Nobel committee decided to award the Nobel prize for medicine in its second year 1902 for malaria research and asked Robert Koch to decide between Grassi and English army physician Ronald Ross. Koch had had a major disagreement with Grassi so chose Ross, even though his work was mainly on birds. Since then the medical establishment has not looked for any other cause.

Malaria Rapid Diagnostic Tests are Poorly Understood but Used Anyway

In MalariaWorld this week there is a discussion of the use of malaria rapid diagnostic tests (RDTs) in Republic of Congo. ‘Low practical knowledge but high willingness to use malaria rapid diagnostic tests among healthcare workers in the Republic of Congo’ by Baina et al is a survey of healthcare worker (HCW) knowledge about use of RDTs for malaria diagnosis. A total of 211 HCWs participated in the study. Nurses comprised the largest group (38%), followed by laboratory technicians (25%), midwives (19%), health assistants (5.7%) and Physicians (4.7%).

96% reported using RDTs, although only 36% had received specific training. General malaria knowledge was low, with just 9% scoring good. Most (90%) had poor understanding of target antigens and diagnostic procedures. 97% perceived RDTs as easy to use and 59% as reliable. In practice, 85.8% used both RDTs and microscopy, but only 7.6% followed national guidelines. No significant associations were found between knowledge, attitudes or practices and demographic or professional characteristics.

Following negative RDTs in symptomatic patients, healthcare workers demonstrated variable responses. 39% requested microscopy, and 27% prescribed antimalarials based on clinical suspicion. Similar observations were seen in studies in other countries. The routine use of confirmatory microscopy following negative RDTs, though sometimes necessary, also places a financial burden on the health system.

It is notable 73.9% prescribed antimalarial treatments after a positive test result so 26.1% did not which concerned the authors.  The authors opine that this gap may reflect persistent doubts about test reliability, limited adherence to guidelines, or reliance on clinical judgment over laboratory confirmation. They note that similar patterns have been reported in other African settings.

Although RDT usage is widespread among healthcare workers in Brazzaville department, significant gaps persist in their knowledge, attitudes, and practices regarding national diagnostic protocols. It seems clear that while they are used because they are easy to use, the HCWs do not necessarily understand them or always believe the result.

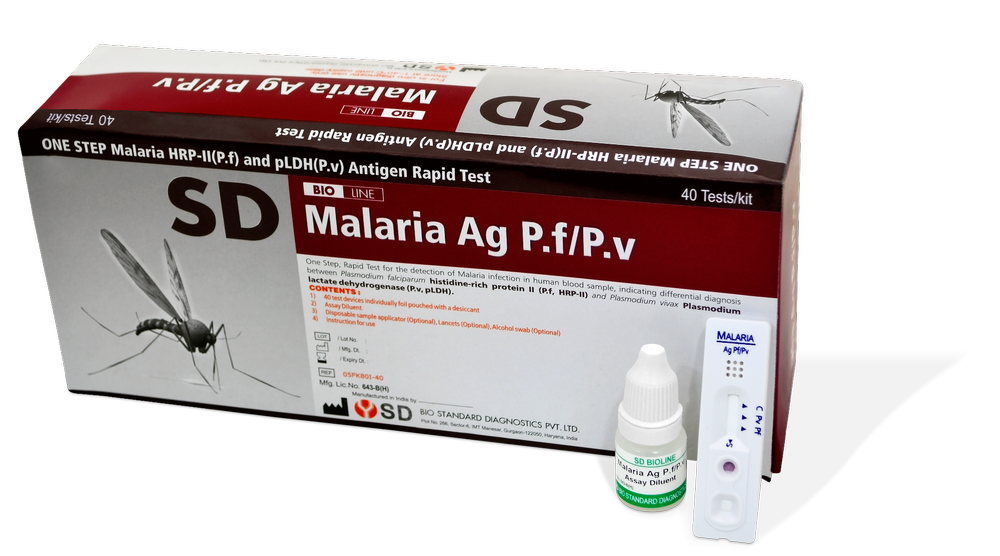
(An interesting footnote is that the main funder of the study was Abbott Rapid Diagnostics, even though their tests did not feature. The most popular RDTs used were two tests from Korean company SD followed by First Response, an Indian product. Abbott was highly favoured in the Internet search that we did to get the RDT picture because of Bioline tag. However, we do not think there is any connection to SD Bioline. And when searching for Abbott separately we found a paper ‘Investigating the Abbott-Bioline™ malaria antigen Pf/Pv rapid diagnostic test’ by Aung et el which has a surprisingly damning conclusion – ‘The Abbott-Bioline™ Malaria Ag Pf/Pv RDT that were obtained in 2024 failed to detect microscopically confirmed cases of malaria and is not fit for purpose. This test should no longer be used and should be replaced by one with adequate performance’.)

Malaria Declining in Bangladesh with Seasonal Variation

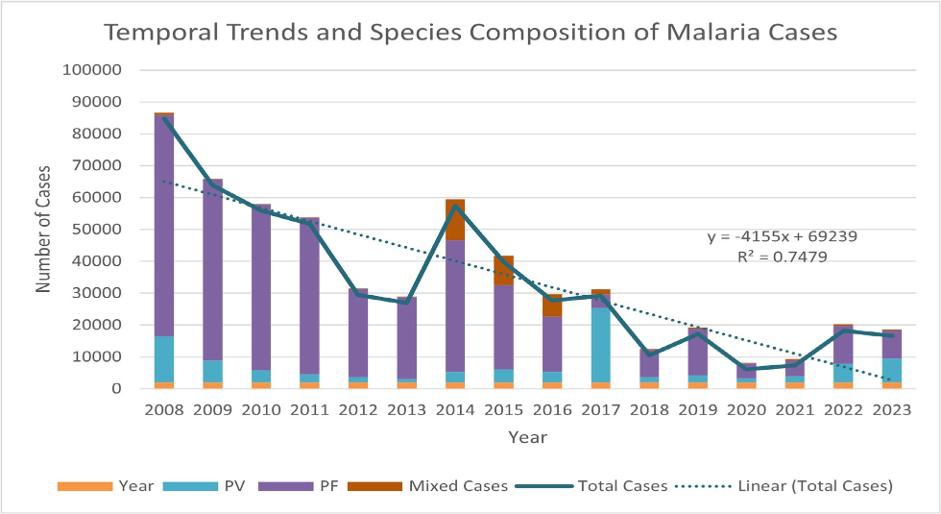
In MalariaWorld this week there is a report with data showing that malaria has declined this century in Bangladesh with seasonal variation of occurrence. ‘Long‑term associations between seasonal variability and malaria transmission in Bangladesh: a 16‑year national time‑series analysis’ by Akter et al is a retrospective ecological time-series study conducted using monthly malaria surveillance data from Bangladesh between January 2008 and December 2023.

Malaria incidence showed a marked long-term decline and a consistent seasonal pattern, with transmission peaking during the monsoon months (July–September). There were over 80,000 cases in 2008 and this has dropped to fewer than 20,000 annual cases 2018-2023. More cases are recorded in the months of June-September, peaking in July. This corresponds to the monsoon, rainy, season. The authors found a significant correlation with relative humidity and lagged rainfall.

It has been previously observed that malaria incidence is higher in rainy seasons and this is discussed in my book ‘Malaria is spread by mosquitos?’. The usual explanation based on the mosquito transmission hypothesis is that such conditions favour mosquito breeding increasing the number female Anopheles mosquitos looking for a blood meal. But it is very important to understand that correlation is not causation and this rule is particularly important when examining regular seasonal patterns. Many other factors vary with the calendar – such as harvest seasons. Also, water might be more likely to be contaminated during the rainy season.

The best news to take from this study is the decline of the incidence of malaria. This multiannual decline is unlikely to be correlated with any mosquito related factor. Malaria has declined in other Asian countries over the last 50 years. As incomes improve occurrence of malaria decreases.

However, the data in this paper show that the incidence has not continued to decline since 2018. And perhaps, unfortunately, if the current middle east crisis results in worldwide food shortages over then next few years the trend may reverse.

If Malaria Disappears Many Will Lose Their Livelihood

MalariaWorld remains on its shorter summer edition and contains no topic of interest not reported previously. Thankfully my email inbox had a thought-provoking article from ‘A Midwestern Doctor’ entitled ‘Why Medicine Won’t Cure You—and How That’s Finally Changing’. The anonymous writer’s substack is a great source of insight of what is wrong with the western medical system from within.

This article focuses mainly on the mental health drugs, SSRIs, and contains the following quotation – ‘When I was in high school, I observed a few discouraging events which led me to postulate: “no industry, organization or cause tasked with solving a problem will actually solve it because the problem disappearing threatens their economic livelihood or political power.” The article continues with reference to a Goldman-Sachs report from 2018 that asked ‘Is curing patients a sustainable business model?’

The same concern applies to malaria. When I worked for a company that produces emergency water treatment products, our sales manager was very envious of a competitor, Vestergaard Frandsen’s, lucrative business selling insecticide treated mosquito nets for malaria. We recently reported on the harm of profligate malaria net distribution and previously on their ineffectiveness at tackling malaria. And if they actually stopped malaria there would be no future business.

The same logic applies to all measures taken to tackle malaria – the drug manufacturers making vaccines, treatments, and prophylactics, the insecticide mosquito sprayers and all the novel research topics using AI, drones or genetically modified insects. What livelihood would they have if malaria were no longer a threat?

Recently, we have found fewer articles that examine the changes that might make a big difference, in particular examining improved nutrition. To address this deficiency, it is the goal of Understand Malaria to become a major funder of research that will discover how to eliminate malaria. And we will proudly state that our number one goal is to solve the problem and put ourselves (and the manufacturers of poisoned nets) out of the malaria business.

If you would like to support this work or know any potential donors who would like to support this research to permanently end the scourge of malaria by attacking he real underlying causes, please contact us.

Wealth Related Inequalities Associated with Malaria

In MalariaWorld this week the most interesting article again discusses the link between malaria and poverty. ‘Prevalence, determinants, and wealth‑related inequalities in malaria among under five children in Uganda: evidence from the malaria indicator survey’ by Mwebesa et al is a secondary analysis of data from the Uganda Malaria Indicator Survey (UMIS) 2018–2019 and finds results similar to the study from Nigeria discussed last week.

Almost 23 in every 100 children under five had malaria infection measured using rapid diagnostic tests (RTD). Regional variations in malaria prevalence and wealth-related inequalities were observed. The multilevel model identified several significant independent factors: older child age (aOR=2.12, 95% CI: 1.51–2.96, P<0.001), child’s anaemia (aOR=3.16, 95% CI: 2.33–4.29, P<0.001), and larger household size (aOR=1.98, 95% CI: 1.13–3.45, P<0.05) were positively associated with malaria in children under five years in Uganda. A negative concentration index (CIX=− 0.334, P<0.001) was also observed, indicating that higher malaria prevalence is concentrated among children in the poorest wealth quintile.

The richest quintile has just 11% of the number of cases observed in the poorest quintile. Anaemic children were over three times more likely to test positive. Anaemia is a strong indicator of malnutrition. Children in households with seven or more were more than twice as likely to test positive as those in households of three or fewer. Refugees were ten times more likely to test positive than urban dwellers. Rural dwellers were over three time more likely to test positive.

There is also detail of the prevalence by region and the regions with highest prevalence with over 50% positive also feature as the poorest areas (e.g. Bugosa, West Nile, Karamoja) found by Uganda National Household Survey 2023/24 reported last year in the Observer (source of picture). Similarly, the areas with lowest poverty (e.g. Kampala, Angole, Kigezi) have among the lowest number of cases.

Mosquitos do not discriminate against the poor. But as long as researchers retain the belief about mosquito malaria transmission they will not focus on measures that would really eliminate malaria. Malaria disappeared from Europe and North America when poverty declined and similarly is disappearing from Asia.